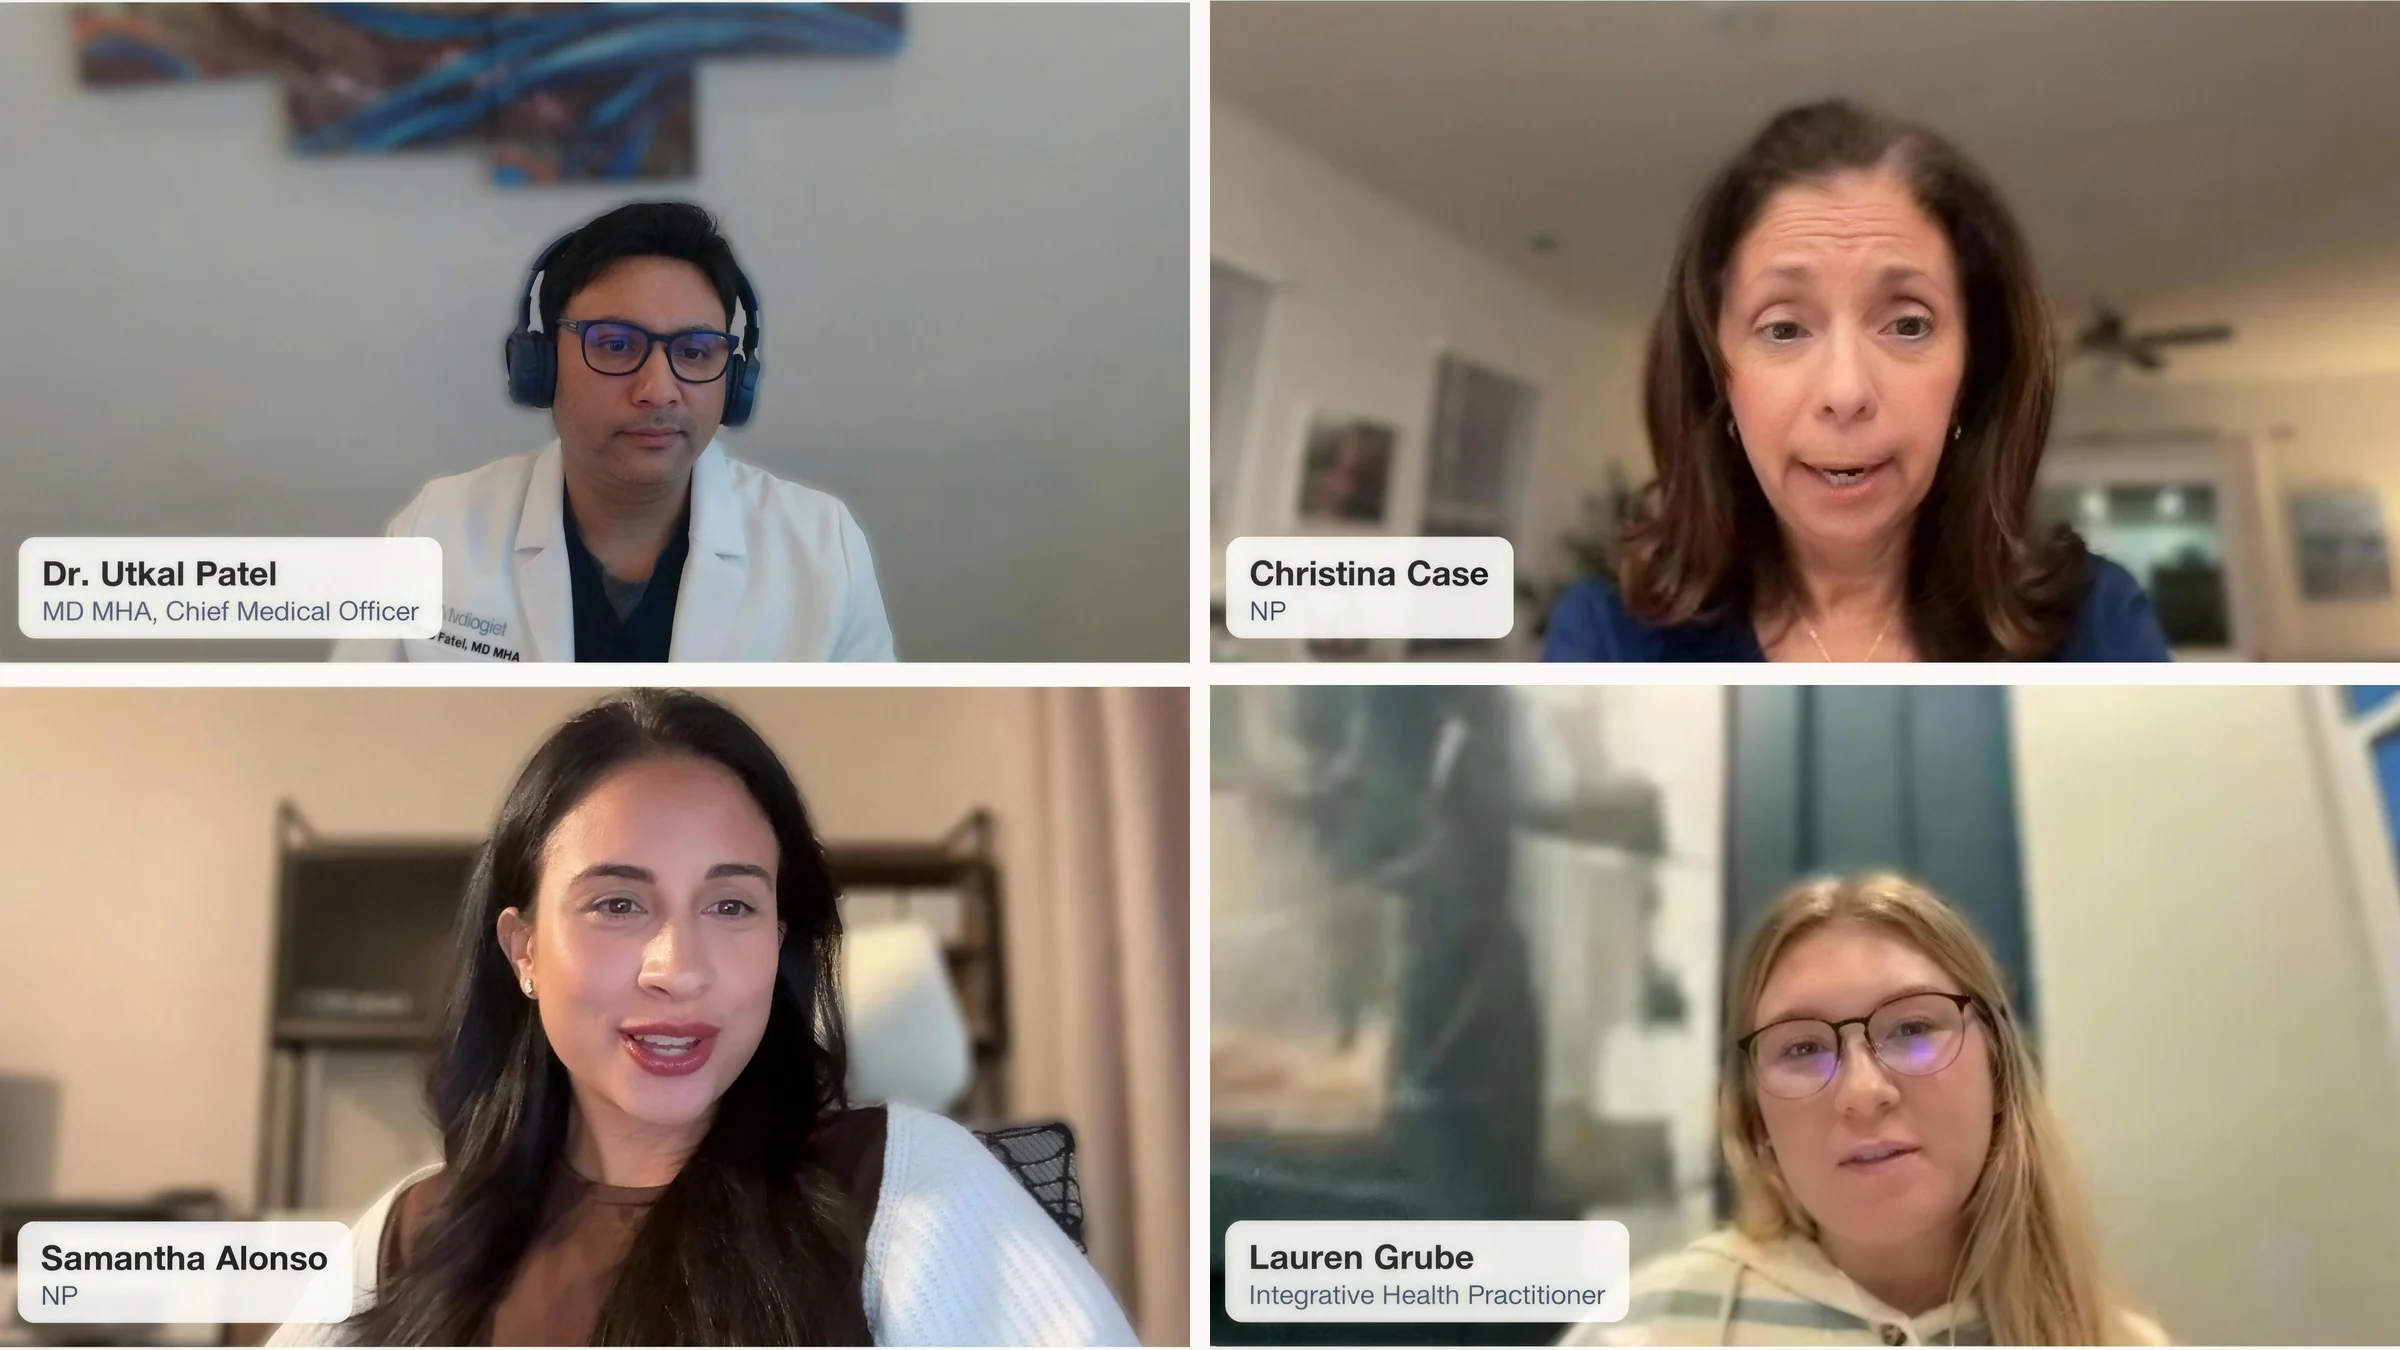
On 14 October 2026, four Ivologist clinicians spent 53 minutes answering 23 questions about hormone replacement therapy and testosterone therapy. Three of the eight audience questions began the same way: my doctor said this is normal for my age. What follows is what the panel said back, organised around the questions people actually ask.
What signs mean you might need HRT?
None of these symptoms belongs to hormones alone. Thyroid disorders, anaemia, medication side effects, depression and sleep disorders can all produce the same picture, which is why the panel kept returning to looking at the whole person rather than one result.
In women
- Waking at night, often around 3am
- New anxiety or irritability
- Worse PMS than previously
- Heavier or more frequent periods
- Breast tenderness
- Brain fog and trouble concentrating
- Joint aches
- Hot flashes and night sweats
- Weight settling around the midsection
In men
The panel was asked whether low testosterone is really just about libido. The answer was no. Fatigue, low motivation, mood changes, brain fog, losing muscle or strength, slower recovery from training, changes in body composition, poor sleep and erectile dysfunction all appear.
Low testosterone is not diagnosed from symptoms or a single number. Symptoms, history, lifestyle and labs are reviewed together, and the panel noted that sleep, stress, thyroid function, insulin resistance, nutrient deficiencies and medications can all produce the same symptoms.
Is this just my age, or is something treatable going on?
This came up more than any other theme across the 53 minutes. One attendee in her 50s described extremely heavy cycles and waking at 3am every morning, and said her provider had told her it was normal at her age. Another, aged 74, had been told that restarting hormones was not recommended. A third had been told to take progesterone in the morning.
In each case the panel's answer was not that the other provider was wrong to be cautious. It was that the question had been closed too early.
Dr Patel put the wider cost plainly: years of fear about HRT caused many women to miss the window for its benefits to heart, bone and brain health.

Perimenopause or menopause? What most people get wrong
The panel's most useful clinical point was about sequence. Progesterone usually drops first, as ovulation becomes irregular, while estrogen swings and can at times run higher than it did in your twenties. That pattern is often called estrogen dominance.
That sequence matters because it changes what the early signs look like. Progesterone is the calming, sleep-supporting hormone, so when it falls first the earliest symptoms are poor sleep and irritability, not hot flashes. Dr Patel noted that many women in their early 40s miss this, because they are watching for hot flashes and getting sleep problems instead.
When does this usually start?
Women can see changes in their 30s and 40s, with most noticing symptoms closer to their 40s. The average age of menopause in the US is about 51. In men, testosterone can begin declining in early to mid adulthood, at different rates in different people.
Why some people start earlier
Genetics play a part, and the panel suggested your mother's age at menopause is a useful clue. Lifestyle matters too: chronic stress, undereating, overexercising, blood sugar imbalance, weight changes and poor sleep. Thyroid problems, certain medications, smoking, alcohol and environmental exposures can all contribute.
Hormone symptoms in your late 20s or 30s do not automatically mean perimenopause. In men, stress, poor sleep and metabolic health can speed up testosterone decline.
What tests should you actually ask for?
| Test | Who | What it shows | Timing note |
|---|---|---|---|
| Reproductive hormones and their regulating signals | Women | Where you are in the transition | Mid-luteal phase, see below |
| Testosterone and related hormones, plus estrogen | Men | Whether levels explain symptoms | Morning draw, confirm a low result with a second test |
| Cortisol rhythm | Both | How cortisol moves across a day | Multiple points, not a single draw |
| Full thyroid panel | Both | Rules out a common mimic | Any time |
| Blood sugar, insulin, cholesterol, metabolic markers | Both | Insulin resistance contributes to hormone imbalance | Fasting |
| Iron panel, vitamin D, B12 | Both | Common, correctable causes of the same symptoms | Any time |
Does the timing in your cycle matter?
Yes, and this is the detail most often missed. Progesterone and estrogen should be checked in the mid-luteal phase, roughly 7 days before your next period. On a 28-day cycle that is days 19 to 21; on a 32-day cycle it is around day 25.
On hormonal birth control, results reflect the medication rather than your own production. Once cycles become irregular in perimenopause, the panel's view was that tracking cycles and symptoms tells you more than any single test.
What about saliva and urine testing?
Blood is the standard starting point for HRT evaluation. Saliva and urine tests can add information, particularly on cortisol rhythm, but are not interchangeable with blood. The panel made a point worth repeating: more testing is not necessarily better, and the test to order is the one that answers the clinical question.
On coverage, the panel's experience was that insurance usually covers blood tests but not saliva or urine tests. That varies by plan.
My labs came back normal but I still feel awful
Labs still earn their place. They rule out thyroid and iron problems, and they monitor dosing safely once treatment starts. The panel's framing was that the goal is treating the patient, not a number on a lab report.

Who is a good candidate for HRT or TRT?
The panel was direct that sometimes another cause should be treated first, and that some conditions and risk factors need more evaluation or make a therapy inappropriate. Their phrase for it was a risk and benefit conversation, not one size fits all.
That framing is worth holding on to in both directions. It argues against being dismissed, and equally against assuming hormones are the answer.
How are hormones given, and when should you take them?
That last point was the panel's emphasis. The best route on paper is not the best route if it does not get used as prescribed.

When to take progesterone
This connects back to the sequence described earlier. If progesterone is the calming, sleep-supporting hormone and it is the first to fall, then timing the dose to work with sleep rather than against it follows logically.
If you have been told something different, that is a conversation to have with your prescriber rather than a reason to change your own dose.
How often should labs be rechecked once you start?
It is individualised. After starting or changing a dose, follow-up usually comes within several weeks to a few months, to check symptoms, side effects and dosing. For women on menopausal hormone therapy, the focus is symptom relief, side effects and blood pressure, and repeat hormone levels are not needed for everyone.
Testosterone needs specific safety monitoring, because it can thicken the blood, which is a cardiovascular concern.
How long before HRT works?
| What changes | Rough timeframe |
|---|---|
| Sleep, mood, hot flashes | Within the first few weeks |
| Energy, libido, general wellbeing | Several months |
| Estrogen and progesterone symptoms, continuing improvement | Through about 3 to 6 months |
| Testosterone effects on libido, energy, body composition | Several months |

Will I be on hormones forever?
Not necessarily. The panel was clear that starting is not a lifelong contract, and that benefit, safety, goals and preference get reassessed over time. Stopping depends on what was taken, for how long, why it started, and current hormone function.
TRT needs an extra conversation. Testosterone taken from outside can suppress the body's own production and affect sperm production and fertility, which matters for younger men or anyone who wants children. Dr Patel added that young men are often steered toward options such as enclomiphene instead, which supports the body's own testosterone production and helps preserve fertility.
What are the risks and benefits?
One safety point is not optional: women with a uterus need progesterone alongside systemic estrogen, to protect the uterine lining.
The FDA has removed some cardiovascular, breast cancer and dementia warnings from black box labeling on some hormone therapies. Even with that change, it does not make HRT right for everyone. The decision still rests on the individual picture.
“I'm in my 50s with heavy periods and waking at 3am. My provider said it's normal.”

New or worsening heavy bleeding needs a workup. The panel named what should be ruled out: fibroids, polyps, thyroid problems, anaemia and endometrial changes. That is a specific list, and it is the kind of thing worth taking to an appointment.
Hormone shifts can drive the sleep disruption, but the panel's position was that the whole picture should be checked rather than assumed. Treatment options include both hormonal and non-hormonal approaches.
If you are past 60 and were told it is too late
But he also named an option he said is often forgotten: local transvaginal estradiol for genitourinary symptoms. It can be used lifelong, is not significantly absorbed into the bloodstream, and needs no blood monitoring.
The panel answered this question broadly rather than as individual advice, and recommended working closely with a primary care provider to rule out other causes such as anaemia and thyroid problems first.
If hormones are not right for you
The panel also pointed to cognitive behavioural therapy and clinical hypnosis, both of which have evidence for menopausal symptoms. And the basics still matter: regular rather than excessive exercise, enough protein, good sleep and stress management.
What the panel said about lifestyle
- Eat enough protein, healthy fats, fibre and nutrients, and keep blood sugar balanced, since insulin resistance contributes to hormone imbalance
- Strength train 3 to 4 days a week and aim for at least 100 g of protein a day
- Avoid chronic undereating, which can dial down hormone production
- Alcohol can worsen sleep and hot flashes
- Overtraining without enough food can disrupt cortisol. The panel's phrase was that more is not better, and doubling up on gym classes can raise cortisol
- Reducing excess midsection fat can improve testosterone in some men, and lower risk for women after menopause
**Dr Patel added a point that explains why lifestyle is not optional here: chronic stress can divert DHEA, a precursor to sex hormones, toward cortisol. Without addressing the stress, replacing hormones may not help much.**

Where to go from here
If your symptoms have been dismissed as just your age, the useful next step is a proper evaluation: history, the right tests at the right point in your cycle, and someone willing to tell you when hormones are not the answer.
Ivologist's Hormone Optimization Program is a 6-month functional medicine programme with 11 health coaching visits and 2 provider visits for lab and medication reviews, medication included as a cream, oral or patch, 2 extensive lab panels including saliva cortisol and hormone testing, a hormone retest at 3 months, and 15% off supplements.
It is not the right route for everyone. If an untreated thyroid condition, anaemia or another identifiable cause has not been ruled out, that comes first. If you want a single prescription without monitoring, this is not that.
**Book a free discovery call on the website, or current patients can ask their provider.**
Frequently Asked Questions
Medical disclaimer. This article summarises a live educational Q&A held on 14 October 2026 and is for informational purposes only. It does not constitute medical advice and is not a substitute for evaluation by a licensed clinician. Questions from attendees were answered as general education rather than individual medical advice. Hormone therapy is prescription-only and requires clinical assessment. Do not start, stop or change any medication based on this article.


